Quick Answer
Yes, in most cases, hair transplant repair is possible, and a well-planned corrective hair transplant can turn an unnatural or failed result into one that looks natural at normal social distance. “Successful” has a specific meaning in repair, though: making the previous work undetectable or substantially less visible, not always recreating the density of a scalp that was never operated on. The outcome depends mainly on how much donor hair remains, the condition of any scarred tissue, and whether the surgeon removes, redistributes, or camouflages the original grafts. Most repairs are staged over 12 to 18 months or longer, and results vary from person to person.
What Counts as a Failed or Botched Hair Transplant?
People searching “hair transplant gone wrong” usually describe one of three situations: the result looks unnatural, the hair never grew as expected, or the donor area now looks thin or scarred. These are clinically different problems, and each has a different repair route.
A widely cited review of repair surgery in Dermatologic Surgery (Bernstein and colleagues, 2002) catalogued these problems, from oversized grafts and poorly placed hairlines to donor scarring and depletion. They fall into three practical groups.
Problems in the Recipient Area
- Pluggy or “doll’s hair” grafts: older large-plug transplants, or modern multi-hair grafts placed at the very front of the hairline, where nature places single hairs.
- A hairline that is too low, too straight, too wide, or too young for the patient’s face and age.
- Hair growing at the wrong angle or in the wrong direction, which cannot be styled to look natural.
- Low density or patchy growth, usually from poor graft survival.
- Surface changes such as ridging, pitting, or cobblestoning around grafts.
Problems in the Donor Area
- Overharvesting: too many follicles extracted, leaving a thin, “moth-eaten” appearance at the back and sides.
- A wide or stretched FUT strip scar.
- Visible FUE dot scarring, often from large punches or dense extraction concentrated in one zone.
Problems of Judgment Rather Than Technique
Some transplants are technically clean but poorly planned. A dense, low hairline created at 22 can look isolated a decade later as the native hair behind it recedes, which is a failure to plan for progressive hair loss rather than a surgical error.
What Does a Failed Hair Transplant Look Like?
| Problem | What It Looks Like | Common Underlying Cause |
|---|---|---|
| Pluggy hairline | Tufts or clumps at the front edge, with visible scalp between them | Large grafts or multi-hair units placed at the hairline |
| Unnatural hairline design | Straight, wig-like, or overly low front line | Design not matched to age, face, or future hair loss |
| Wrong angulation | Hair standing straight up or growing against the natural direction | Incorrect placement angle during implantation |
| Poor growth | Thin, patchy coverage after 12 or more months | Graft damage, dehydration, long out-of-body time |
| Overharvested donor | See-through, uneven back and sides | Extraction beyond what the donor could support |
| Wide FUT scar | Visible line when hair is worn short | Excess tension, poor closure, tight scalp |
Is It a Failure, or Is It Too Early to Judge?
Before calling a transplant a failure, check the calendar. Transplanted hair typically sheds within weeks, enters a dormant phase, and only begins regrowing around months 3 to 4. Frontal results usually mature by about 12 months, and crown results can take up to 18 months.
For this reason, corrective surgeons generally assess a repair case only after the previous procedure has had 9 to 12 months to mature, so the real extent of the problem can be mapped. The exception is any sign of infection, spreading redness, or non-healing skin in the first weeks; these need prompt review by your treating doctor, not a wait-and-see approach. Our guide to how long hair transplant results last covers the normal growth timeline in detail.
Why Hair Transplants Go Wrong
Repair cases are not rare, and their share is rising. The International Society of Hair Restoration Surgery (ISHRS) reported that 5.4% of hair restoration patients sought repair surgery in 2021, up from 4.2% in 2019. In its 2025 Practice Census, ISHRS members reported that, on average, 10% of repair cases were due to a previous black market hair transplant, up from 6% in 2021, and 59% said such clinics operate in their cities.
“Black market” refers to procedures performed by unlicensed or untrained individuals without meaningful physician involvement. ISHRS links these clinics to visible scarring, infection, thin patches, and overharvested donor areas that are often hard to correct. Beyond unlicensed clinics, the common causes are:
- Poor graft handling: long out-of-body time, dehydration, or follicles damaged during extraction (transection).
- Volume-driven planning: maximizing grafts per session rather than planning around lifetime donor supply.
- Hairline design without a long-term view: ignoring how hair loss is likely to progress over the next 10 to 20 years.
How Surgeons Repair Hair Transplant Problems: The Main Corrective Techniques
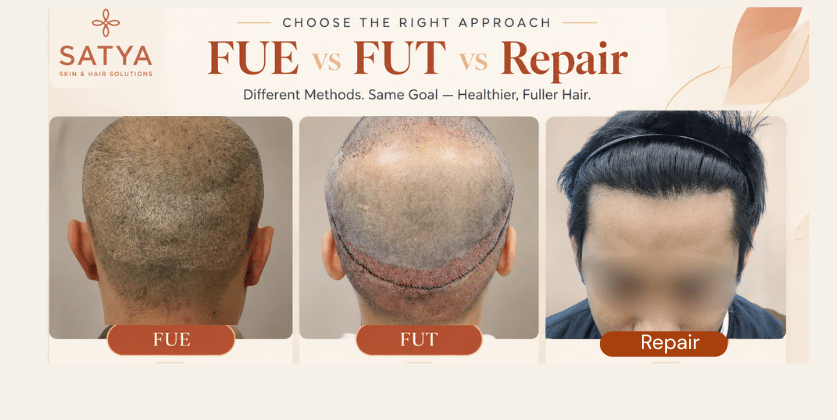
There is no single “repair procedure.” A corrective hair transplant is a set of techniques chosen and sequenced for each case. The 2002 Dermatologic Surgery review describes two core strategies, often combined: camouflaging problem grafts with new, natural-looking follicular units, and removing badly placed grafts so they can be re-implanted correctly.
1. Camouflage With New Follicular Units
Single-hair follicular units are placed in front of and between existing grafts to soften a harsh or pluggy line, recreating the gradual transition a natural hairline has. This uses relatively few donor grafts, which matters when donor supply is limited. It works best when the original hairline sits in an acceptable position but looks too abrupt.
2. Graft Removal and Re-implantation
When grafts are too low, too large, or wrongly angled, camouflage alone cannot fix them. The grafts are extracted, dissected into individual follicular units, and re-implanted in a natural position and direction, so the hair is reused rather than wasted.
Removal is usually staged across sessions. Closely spaced grafts, and the way roots fan outward beneath the skin, make complete removal in one sitting a risk for additional scarring.
3. Laser Hair Removal (Selective Use)
Laser hair removal can eliminate hair from misplaced grafts, but it destroys those follicles and does nothing to improve the scar beneath them; removing the hair can even make that scarring more visible. It is generally reserved for a few grafts that cannot be extracted cleanly.
4. Donor Scar Repair
- FUE into a strip scar: follicles are transplanted directly into a wide FUT scar to break up the line.
- Scar revision: surgically excising and re-closing a wide scar, considered only where scalp laxity allows.
- Scalp micropigmentation (SMP): a medical tattooing technique that adds fine pigment dots to blend scars or a see-through donor area. It is a camouflage tool, not hair, and published experience notes that outcomes vary with technique and materials.
5. Alternative Donor Sources: Beard and Body Hair
When scalp donor hair is depleted, beard and sometimes body hair can supplement a repair. A small Indian comparative study in the Journal of Cutaneous and Aesthetic Surgery (five patients, 150 grafts per hair type) reported one-year survival of 88.7% for scalp grafts, 94.7% for beard grafts, and 75.3% for chest hair grafts.
Because body hair differs from scalp hair in texture, caliber, and growth length, it is usually most useful behind the hairline or in scars, not at the hairline itself.
6. Medical and Supportive Management
Repairing a transplant without stabilizing ongoing native hair loss can mean repeating the problem later. Medical management, adjunct therapies such as PRP or GFC to support native hair, and SMP are often part of a complete corrective plan, decided case by case.
Matching the Problem to the Approach
| Problem | Common Corrective Approach | Main Limitation |
|---|---|---|
| Pluggy hairline | Staged removal, re-implantation, camouflage with single-hair units | Usually needs more than one session |
| Hairline too low | Graft removal and re-implantation | Removal can leave fine scars; staged |
| Hairline too high or too thin | New follicular units for definition and density | Depends on remaining donor supply |
| Wrong angles | Extraction and re-angled re-implantation | Not every graft can be salvaged |
| Poor growth | Repeat grafting with careful handling, after maturation | Scarred recipient tissue may reduce survival |
| Wide FUT scar | FUE into the scar, revision, SMP | Rarely invisible with very short hair |
| Overharvested donor | Redistribution, beard or body hair, SMP | Extracted follicles cannot be replaced |
The Biggest Constraint in Any Repair: Your Remaining Donor Supply
The 2002 repair review identified limited donor supply as the main barrier to complete correction. Donor follicles do not regenerate once extracted, so a donor area overused in the first surgery leaves less material for the second.
Published FUE guidance shows how narrow the margin is. A 2018 study of donor-area effects recommended limiting FUE to less than 35% of total hair density in a first session and no more than 10 to 20% in a second, warning that removing around half of donor density approaches the point where thinning becomes visible.
“A patient can survive a bad hairline. A patient cannot survive a destroyed donor.” Dr. Shail Gupta
This is where our MHT™ (Maximum Harvesting Technique) planning approach applies to repair: maximizing usable yield from what remains while protecting donor aesthetics, not extracting the most grafts possible in one sitting.
Why Grafts Behave Differently in Scarred Tissue
A first transplant is placed into healthy, well-vascularized scalp. A repair often is not. Scarred skin has a compromised microvascular supply, and newly placed grafts depend on that supply to survive their first days, before new blood vessels form around them.
A 2025 review in Surgeries on transplantation into scarring alopecias notes that reduced blood flow and tissue hypoxia lower graft survival compared with non-scarred scalp, and recommends lower initial densities of about 20 to 25 grafts per square centimetre. A 2025 case series in the Journal of Cutaneous and Aesthetic Surgery reported outcomes consistent with literature figures of 60 to 85% graft survival in scarred scalp using FUE and staged sessions. For comparison, roughly 90 to 98% survival is commonly cited for well-executed primary procedures.
These figures come largely from scarring hair loss conditions and post-surgical scars rather than transplant repairs alone, but the underlying biology is comparable. The practical consequences for a corrective hair transplant are:
- Conservative density per session, rather than packing grafts into compromised tissue.
- Staged sessions, so each stage can heal and its blood supply can mature before the next.
- Careful graft handling, because grafts entering a weaker recipient bed have less margin for added stress. Our DSFT™ protocol focuses on minimizing out-of-body time and repeated handling for this reason.
What Does a “Successful” Hair Transplant Repair Actually Mean?
Success in repair is best defined before surgery, in writing, against your own priorities. The 2002 review recommends ranking the patient’s concerns and confirming which are realistically achievable, rather than imposing the surgeon’s aesthetic preferences.
| Repair Goal | Is It Usually Achievable? | What Determines It |
|---|---|---|
| Making a pluggy hairline look natural at normal social distance | Often, with staged removal and camouflage | Number and size of plugs, donor supply |
| Correcting a hairline placed too low | Often, but harder than lowering a high one | Removal needed; fine residual scarring possible |
| Improving density after poor growth | Often, partially or fully | Remaining donor supply, scar quality |
| Making a wide FUT scar much less visible | Often | Scar width, scalp laxity, hair length worn |
| Reversing overharvesting | Partially at best | Extracted follicles cannot be replaced |
| Matching a never-operated scalp exactly | Rarely, in severe cases | Extent of the previous damage |
There is an important asymmetry here. A hairline placed too high can usually be brought forward with new grafts, while a hairline placed too low has to be taken apart, which is slower, staged, and more demanding. This is one reason we design first-time hairlines conservatively.
The Clinical Journey of a Corrective Hair Transplant
Before: Assessment and Planning
- Timing: usually at least 9 to 12 months after the previous surgery, so growth has matured.
- Records: previous surgical notes, graft counts, and dated photographs, where available.
- Trichoscopic and donor assessment: donor density, hair caliber, scalp laxity, and existing scarring.
- Priority ranking: which concern matters most to you, and which goals are realistic.
- Medical stabilization: assessing and managing ongoing native hair loss before further surgery.
During: Staged Procedures
Corrective procedures are performed under local anaesthesia, like a primary transplant. A complex case may involve a removal stage, a re-implantation or camouflage stage, and later density refinement, each spaced months apart. Simpler cases, such as softening a well-positioned but abrupt hairline, may need a single session.
After: Recovery and Realistic Timelines
Immediate recovery broadly mirrors a standard transplant (see our guide to hair transplant pain and recovery), though removal sites and scarred tissue may need extra healing time.
| Timeframe (Per Stage) | What to Expect |
|---|---|
| Weeks 1 to 2 | Removal and implantation sites heal; mild redness |
| Weeks 2 to 6 | Newly transplanted hair shafts shed (expected) |
| Months 3 to 4 | Early regrowth begins |
| Months 6 to 9 | Visible improvement; progress reviewed |
| Months 12 to 18 | Stage matures; final assessment before any next stage |
For complex repairs involving several stages, the full corrective journey can extend beyond two years. We state this up front because a rushed repair on a compromised scalp is how a second problem gets created.
How to Choose a Surgeon for Hair Transplant Correction
Repair is more technically and strategically demanding than a first transplant, so the selection criteria should be stricter:
- The surgeon performs the critical steps, including hairline design and graft removal, rather than delegating the case to technicians.
- Documented repair cases with dates, showing follow-up of 12 months or longer, shared with patient consent.
- A donor-first assessment before any graft number is discussed.
- A written, staged plan that states what is and is not achievable for your scalp.
- Willingness to recommend less, including camouflage, medical management, or no further surgery, when that is the right answer.
Where Satya Stands on Hair Transplant Repair
Corrective work follows the same principles as every procedure at Satya, with less margin for error: donor before density, natural before dense, strategy before surgery. Hairline redesign follows our Mimic Nature Hairline™ approach, built around facial proportions, age, and how the hairline will age with you. Donor use follows MHT™ planning, graft handling follows DSFT™, and supporting medication follows MIN-MED™, the lowest effective dose your case requires.
We would rather tell you that a partial improvement is the honest ceiling for your scalp, or that camouflage is wiser than another extraction, than promise a result your donor supply cannot support.
Frequently Asked Questions
In most cases, yes. Pluggy hairlines, poor angles, low density, and donor scars can usually be improved substantially through removal, re-implantation, camouflage, or scar repair. How complete the correction can be depends mainly on remaining donor supply and the condition of any scarred tissue.
Usually at least 9 to 12 months after the previous surgery, so the transplanted hair has had time to grow and the true result can be assessed. Signs of infection or non-healing skin are the exception and should be reviewed by a doctor promptly.
Yes, but it is more demanding than lowering a high hairline. Grafts placed too low are generally removed in stages and re-implanted in a more appropriate position, sometimes with laser hair removal for grafts that cannot be extracted cleanly.
A wide FUT scar or FUE dot scarring can usually be made much less visible using FUE grafting into the scar, surgical revision where scalp laxity allows, or scalp micropigmentation. Scars cannot be erased, so how visible they remain depends partly on how short you wear your hair.
Extracted follicles cannot be replaced, so overharvesting cannot be fully reversed. Appearance can often be improved by redistributing remaining hair, adding beard or body hair where suitable, and using SMP to reduce the see-through effect.
Often not quite as well as in an untouched scalp. Published figures for scarred scalp commonly fall in the 60 to 85% range, below the 90 to 98% cited for well-executed primary procedures, which is why repairs use lower densities and staged sessions.
There is no fixed price, because cost depends on whether grafts must be removed, how many new grafts are needed, and the number of stages. A responsible estimate follows a donor and scar assessment; our guide to hair transplant cost in Delhi explains graft-based pricing in general.
An Evidence-Based Next Step
A second surgery on a compromised scalp deserves more planning than the first, not less. If you are unhappy with a previous transplant and want an honest assessment of what can be corrected, what cannot, and over how many stages, schedule an evidence-based consultation with our hair restoration team at Satya Skin & Hair Solutions, Gurgaon & Delhi. Please bring any surgical records and dated photographs you have. Results vary from person to person, and any recommendation will be based on your donor and scalp assessment, not a standard package.